
Category: Complex Dysphagia

Resources and case discussions on complex and long-standing swallowing difficulties, tube weaning and second-opinion cases.

  • Swallowing After Brainstem Stroke (Lateral Medullary Syndrome): Why Careful Retraining Matters

    In short: A stroke in the brainstem, especially lateral medullary syndrome (Wallenberg syndrome), can cause some of the most severe swallowing difficulties seen after stroke. People may feel they have “forgotten how to swallow”: the swallow will not start, or it starts but the muscles work in the wrong order. Because swallowing is a finely timed skill, therapy needs a careful plan that helps the person understand and recognise their own swallow. Surface EMG (sEMG) biofeedback is often a valuable part of this retraining. Without the right approach, people can learn poor swallowing habits that make swallowing worse.

    Why brainstem stroke affects swallowing so severely

    The swallowing control centre sits in the medulla, the lowest part of the brainstem. It works like a conductor: once a swallow is triggered, it switches many muscles in the mouth, throat and voice box on and off in a precise sequence within about a second. In lateral medullary syndrome, the stroke damages this area, so:

    • The swallow may not start, even when the person is trying hard to swallow
    • The sequence breaks down: muscles fire too early, too late or not together
    • The upper oesophageal sphincter may not open properly, so food and saliva cannot pass into the food pipe
    • One side of the throat may be weak, so food collects on that side
    • Food, drink or saliva may enter the airway (aspiration), sometimes without a cough

    Other signs of lateral medullary syndrome can include a hoarse voice, dizziness, unsteadiness, hiccups and changes in sensation on the face or body. Many people cannot swallow their own saliva at first and need tube feeding.

    Why swallowing must be retrained carefully

    After a brainstem stroke, the problem is often not only weakness but coordination: the timing and order of the swallow. Retraining coordination is a skill-learning process, much like relearning a precise movement after an injury.

    This is why the approach matters. If a person keeps attempting swallows that are poorly timed or uncoordinated, the brain can “practise the wrong pattern”. People may develop maladaptive swallowing behaviours, such as using excessive force, holding their breath in the wrong way, jerking the head, or swallowing repeatedly without clearing the throat. These habits can become established and make swallowing less effective and less safe, and harder to correct later.

    Good therapy therefore starts with a careful plan:

    • A detailed assessment, often including FEES, to see exactly which part of the swallow is breaking down
    • Helping the person understand and recognise their own swallow: what a correct swallow should feel like, and how it differs from an ineffective attempt
    • Practising the right pattern in small, achievable steps, usually starting with saliva swallows before food or drink
    • Adding food and drink only when it is safe, with the right textures and strategies
    • Regular reassessment and progression, including weaning from tube feeding when ready

    How sEMG biofeedback helps

    Surface EMG biofeedback uses small sticky sensors on the skin under the chin to show the activity of the swallowing muscles on a screen in real time. It is painless and non-invasive.

    Speech therapist showing a patient their swallowing muscle activity on an sEMG biofeedback screen
    Showing a patient their swallow on the sEMG screen in real time
    • It makes the swallow visible. The person can see when the swallow starts, how strong it is and how long it lasts.
    • It gives instant feedback, so a correct swallow can be recognised and repeated, and an incorrect one corrected straight away.
    • It allows precise targets for strength and timing, which the therapist adjusts as swallowing improves.
    • It shows progress session by session, which helps motivation.

    Research supports this approach. A retrospective study of people with chronic dysphagia after brainstem stroke reported improved swallowing with intensive therapy using sEMG biofeedback, and a study of 45 patients found that 87% increased their oral intake after therapy supplemented with sEMG biofeedback, with the best results in the stroke group (92%). In our experience, biofeedback often gives an added advantage in both therapy and prognosis for brainstem stroke.

    Can swallowing recover after lateral medullary syndrome?

    Many people with lateral medullary syndrome regain the ability to eat and drink by mouth, although recovery can take weeks to months. Even people who are still tube-fed many months after their stroke can improve with a well-planned, intensive programme. The key is early assessment and therapy that trains the right swallowing pattern from the start.

    How we can help

    We provide assessment and therapy for complex swallowing difficulties after brainstem stroke, including FEES, sEMG biofeedback therapy, family and caregiver training, and second opinions when progress has stalled. Contact us to arrange an assessment.

    Frequently asked questions

    Why can’t I swallow even though I am trying?

    In lateral medullary syndrome, the brainstem centre that triggers and coordinates the swallow is damaged. The muscles may still have strength, but the signal to start the swallow and the timing between muscles are disrupted. Therapy aims to retrain this.

    Should I keep practising swallowing on my own?

    Only as advised by your speech therapist. Unsupervised attempts with poor timing can lead to aspiration and can reinforce the wrong swallowing pattern. Your therapist will tell you exactly what to practise and how.

    What is sEMG biofeedback, and does it hurt?

    Small sensors are placed on the skin under the chin to show swallowing muscle activity on a screen. It does not hurt and nothing is inserted. It helps you see and learn the correct swallow.

    Is it too late if my stroke was many months ago?

    Not necessarily. Improvement has been reported even in chronic brainstem dysphagia with intensive, well-targeted therapy. An assessment will show what is possible.

    Will I need a feeding tube?

    Many people need tube feeding at first to stay nourished and safe. The goal of therapy is to rebuild a safe swallow and reduce or remove the need for the tube when possible.

    References

    • Huckabee, M.L., & Cannito, M.P. (1999). Outcomes of swallowing rehabilitation in chronic brainstem dysphagia: A retrospective evaluation. Dysphagia, 14(2), 93–109.
    • Crary, M.A. (1995). A direct intervention program for chronic neurogenic dysphagia secondary to brainstem stroke. Dysphagia, 10(1), 6–18.
    • Crary, M.A., Carnaby, G.D., Groher, M.E., & Helseth, E. (2004). Functional benefits of dysphagia therapy using adjunctive sEMG biofeedback. Dysphagia, 19(3), 160–164.

    Written by Yoon Wai Lam, Director and Senior Principal Speech Therapist, B.Speech Sc. (Hons), in clinical practice since 2001, who set up the sEMG biofeedback framework for swallowing therapy at Singapore General Hospital. This article is for general information and does not replace an individual assessment. Contact us to discuss a specific case.

  • Swallowing After Radiotherapy for Nasopharyngeal Cancer (NPC): Long-Term Effects and How to Protect Your Swallow

    In short: Radiotherapy for nasopharyngeal cancer (NPC) can affect swallowing not only during treatment but for many years afterwards. Over time, radiation can cause the muscles and tissues of the mouth and throat to stiffen (fibrosis) and can damage the nerves that control swallowing. This is called late radiation-associated dysphagia. Starting a swallowing preservation programme before radiotherapy, continuing it during and after treatment, and having regular swallowing reviews for life can help protect swallowing and catch problems early.

    Why NPC radiotherapy affects swallowing in the long term

    Radiotherapy for NPC targets the back of the nose, the skull base and the lymph nodes in the neck. The treatment area often includes the upper throat muscles, the soft palate, the base of the tongue and nearby nerves. Modern techniques such as IMRT reduce the dose to these structures, but some exposure is usually unavoidable.

    • Fibrosis: treated muscles and soft tissues can gradually become stiff and weak. This may continue to progress for years after treatment ends.
    • Nerve damage (lower cranial neuropathy): the nerves that control the throat, voice and tongue (cranial nerves IX, X and XII) can be affected, sometimes many years later. This can cause tongue weakness, a hoarse or weak voice, and poor throat squeeze.
    • Dry mouth (xerostomia): reduced saliva makes chewing and moving food harder.
    • Trismus: stiffness of the jaw muscles can limit mouth opening.
    • Reduced throat sensation: food or drink may enter the airway without triggering a cough. This is called silent aspiration.

    Because these changes can develop slowly, many NPC survivors swallow well for years and then notice problems 5, 10 or even more years after radiotherapy.

    Signs to look out for

    • Coughing or choking during or after meals or drinks
    • A wet or gurgly voice after swallowing
    • Food sticking in the throat, or needing several swallows for each mouthful
    • Meals taking much longer, or avoiding certain foods
    • Food or liquid coming back through the nose
    • Unplanned weight loss
    • Repeated chest infections or pneumonia
    • Slurred speech, a weak voice or difficulty moving the tongue
    • Difficulty opening the mouth

    Repeated chest infections can be a sign of silent aspiration, even without obvious coughing during meals. An instrumental assessment such as FEES can show whether food or drink is entering the airway.

    The swallowing preservation protocol

    Swallowing preservation means looking after swallowing at every stage: before, during and after radiotherapy, and for life. The aim is to keep the swallowing muscles working, avoid long periods without eating or drinking by mouth, and pick up changes early.

    Before radiotherapy

    • Baseline swallowing assessment by a speech therapist, with FEES if needed, so later changes can be compared
    • Education for the patient and family on how radiotherapy may affect swallowing, short and long term
    • Start swallowing exercises and learn to do them correctly
    • Measure mouth opening and start jaw stretches if there is a risk of trismus
    • Dental review and nutrition advice as part of the cancer team’s care

    During radiotherapy

    • Keep eating and drinking by mouth as much as is safe, even if textures need to be softer. Muscles that are not used weaken quickly: “use it or lose it”.
    • Continue swallowing exercises daily, adjusted for pain and fatigue
    • Regular review by the speech therapist to adjust textures and strategies
    • Good pain control and mouth care, working with the oncology team, so swallowing can continue
    • If a feeding tube is needed, keep swallowing small amounts safely when advised, so the muscles stay active

    In the months after radiotherapy

    • Rebuild swallowing: continue exercises and gradually return to a normal diet
    • Wean off the feeding tube as soon as it is safe
    • Reassess swallowing, including FEES where needed, as swelling settles
    • Continue jaw stretches to prevent or reduce trismus

    Long term: for life

    • Maintenance exercises as advised by your speech therapist, even when swallowing feels normal
    • A swallowing review at least once a year, or sooner if anything changes
    • Act early on new symptoms: late swallowing changes are easier to manage when caught early
    • Good oral hygiene, which reduces the risk of chest infection if aspiration occurs
    • Keep a healthy weight and watch for unplanned weight loss

    Exercises and therapies that may help

    Therapy is planned after an assessment, because the right exercises depend on which parts of swallowing are affected. Options may include:

    • Chin Tuck Against Resistance (CTAR) to strengthen the muscles under the chin that help open the food pipe
    • Effortful swallow, tongue strengthening and tongue-hold (Masako) exercises for throat squeeze and tongue base movement
    • The Mendelsohn manoeuvre to prolong opening of the food pipe
    • Jaw stretching exercises for trismus
    • Expiratory muscle strength training (EMST) to strengthen coughing and airway protection
    • Surface EMG (sEMG) biofeedback, which shows muscle activity on a screen to help you exercise more accurately
    • Safe swallowing strategies and texture changes to reduce the risk of aspiration

    About the research: the large PRO-ACTIVE trial (952 patients receiving radiotherapy for head and neck cancer) found that feeding tube use was lower than expected and swallowing outcomes were favourable in all groups that received swallowing therapy support, whether exercises were started early or later, and whether therapy was more or less intensive. Keeping patients eating, drinking and exercising with speech therapy support is the common thread.

    How we can help

    We provide home-based and clinic swallowing assessments, FEES, sEMG biofeedback therapy and second opinions for complex dysphagia, including long-standing swallowing difficulties many years after NPC treatment. Contact us to arrange an assessment.

    Frequently asked questions

    Can swallowing problems start many years after radiotherapy for NPC?

    Yes. Fibrosis and nerve damage from radiotherapy can develop slowly, so some people first notice swallowing problems 5, 10 or more years after treatment. New swallowing symptoms should be checked, even if treatment was long ago.

    Is it too late to start swallowing exercises years after treatment?

    No. Exercises and other therapies can still improve or maintain swallowing for many people. A swallowing assessment helps decide which approach is likely to help.

    What is silent aspiration?

    Silent aspiration is when food, drink or saliva enters the airway without causing a cough. It is common after head and neck radiotherapy because throat sensation can be reduced, and it can lead to chest infections. FEES can detect it.

    Will I need a feeding tube?

    Not everyone does. Keeping up oral intake and swallowing exercises with speech therapy support helps many people avoid a tube or use one for a shorter time. If a tube is needed, it is usually best to keep swallowing safely as advised.

    How often should I have my swallowing checked after NPC treatment?

    We recommend a swallowing review at least once a year for NPC survivors, and sooner if you notice coughing, food sticking, weight loss or chest infections.

    References

    • Hutcheson, K.A., Lewin, J.S., Barringer, D.A., et al. (2012). Late dysphagia after radiotherapy-based treatment of head and neck cancer. Cancer, 118(23), 5793–5799.
    • Patterson, J.M. (2019). Late effects of organ preservation treatment on swallowing and voice; presentation, assessment, and screening. Frontiers in Oncology, 9, 401. doi:10.3389/fonc.2019.00401
    • Hutcheson, K.A., Fuller, C.D., Pytynia, K.B., et al. (2025). PRO-ACTIVE: Results of a pragmatic phase IV randomized trial comparing the effectiveness of prophylactic swallow intervention for patients receiving radiotherapy for head and neck cancer. Journal of Clinical Oncology, 43(17_suppl), LBA12000.
    • Liu, W.S., Chien, J.C., Huang, Y.H., et al. (2022). High superior-middle pharyngeal constrictor muscle mean dose correlates with severe late lung infection and survival in nasopharyngeal cancer patients. Cancer Management and Research, 14, 1063–1073.
    • Yoon, W.L., Khoo, J.K.P., & Rickard Liow, S.J. (2014). Chin Tuck Against Resistance (CTAR): New method for enhancing suprahyoid muscle activity using a Shaker-type exercise. Dysphagia, 29(2), 243–248.

    Related articles: Chin Tuck Against Resistance (CTAR): A Guide from the Originator · Swallowing After Brainstem Stroke (Lateral Medullary Syndrome)


    Written by Yoon Wai Lam, Director and Senior Principal Speech Therapist, B.Speech Sc. (Hons), in clinical practice since 2001 and originator of the CTAR swallowing exercise. This article is for general information and does not replace an individual assessment. Contact us to discuss a specific case.
  • Chin Tuck Against Resistance (CTAR): A Guide from the Originator

    Chin Tuck Against Resistance (CTAR): A Guide from the Originator

    In short: Chin Tuck Against Resistance (CTAR) is a swallowing exercise that strengthens the suprahyoid muscles, the muscles under the chin that pull the hyoid bone up and forward during swallowing, which helps open the upper oesophageal sphincter so food and drink can pass into the food pipe. It is done sitting or standing, by tucking the chin down firmly against a small rubber ball. CTAR was developed by Singapore speech therapist Yoon Wai Lam and first published in the journal Dysphagia in 2014.

    Why CTAR was developed

    For many years, the Shaker (head-lift) exercise was the standard way to strengthen the suprahyoid muscles. It requires lying flat on the back and repeatedly lifting the head, which many people find tiring and hard on the neck. It is especially difficult for older adults, people who are frail or bedbound, and those who cannot lie flat.

    CTAR was designed to train the same muscles in an upright position, using a simple rubber ball for resistance. This makes it practical to do at home, in a chair or at the bedside, with very little equipment.

    How to do CTAR

    You will need: a rubber ball about 12 cm in diameter for most adults. The right size depends on the length of your neck, so your speech therapist will advise. A ball pump can be used to adjust the firmness.

    Part 1: Sustained CTAR (isometric)

    1. Sit or stand upright with your shoulders back. Keep this posture throughout.
    2. Hold the ball under your chin with one hand.
    3. Tuck your chin down against the ball as hard as you can, and hold for 60 seconds.
    4. Rest for 1 minute.
    5. Repeat for a total of 3 sets, twice a day.

    Part 2: Repetitive CTAR (isokinetic)

    1. Keep the same upright posture, with the ball under your chin.
    2. Tuck your chin down hard against the ball, then lift your chin.
    3. Repeat 60 times, or as recommended by your speech therapist. Rest briefly if you need to.
    CTAR with a rubber ball, demonstrated by its originator. Also available in Mandarin, Malay, Korean, Japanese, Taiwanese Minnan and Bengali.

    What the research shows

    • 2014, the original study (Yoon, Khoo & Rickard Liow, Dysphagia): In 40 healthy adults, surface EMG showed that CTAR activated the suprahyoid muscles significantly more than the Shaker exercise during the sustained (isometric) task, and at least as much during the repetitive (isokinetic) task. The study won First Place for Scientific Abstract at the 21st Annual Meeting of the Dysphagia Research Society, Seattle (2013).
    • 2016, training effects (Sze, Yoon, Escoffier & Rickard Liow, Dysphagia): compared the training effects of CTAR and the Shaker exercise using surface EMG. In 39 healthy adults, CTAR targeted the suprahyoid muscles more specifically than the Shaker exercise and fatigued them equally or more, while the sternocleidomastoid (a large neck muscle) was significantly less activated and less fatigued. In other words, CTAR works the swallowing muscles hard while putting less strain on the neck.
    • 2017, Swallow with CTAR (S-CTAR): combines a swallow with CTAR to make the exercise more task-specific to swallowing (Dysphagia Research Society, Portland).
    • CTAR has since been studied and used by clinicians and researchers in many countries.

    Who CTAR can help

    After a swallowing assessment, CTAR may be included in therapy for adults with weak swallowing muscles, for example:

    Safety: do it with professional guidance

    CTAR should be prescribed after a proper swallowing assessment by a speech therapist, who will check that it suits your condition and set the right ball size, effort and number of repetitions. Stop and seek advice if you feel neck pain, dizziness or discomfort. If you have neck or spine problems, check with your doctor or therapist first. Exercises like CTAR are one part of swallowing therapy and do not replace advice on safe food and drink textures.

    Frequently asked questions

    What is the difference between CTAR and the Shaker exercise?

    Both strengthen the suprahyoid muscles. The Shaker exercise is done lying flat and lifting the head, while CTAR is done sitting or standing by tucking the chin against a ball. Many people find CTAR easier to do and less tiring for the neck.

    How often should I do CTAR?

    A common programme is a 60-second hold repeated 3 times, plus 60 repetitive chin tucks, twice a day. Your speech therapist may adjust this to suit you.

    What size ball should I use?

    About 12 cm in diameter suits most adults, but the best size depends on the length of your neck. Your therapist will check the fit.

    Can I do CTAR without seeing a speech therapist?

    It is best to have a swallowing assessment first. Swallowing difficulties have many causes, and a therapist can tell you whether CTAR is right for you and how to do it safely.

    Where can I find a CTAR video in my language?

    The video above is also available in Mandarin, Malay, Korean, Japanese, Taiwanese Minnan and Bengali.

    References

    • Yoon, W.L., Khoo, J.K.P., & Rickard Liow, S.J. (2014). Chin Tuck Against Resistance (CTAR): New method for enhancing suprahyoid muscle activity using a Shaker-type exercise. Dysphagia, 29(2), 243–248. doi:10.1007/s00455-013-9502-9
    • Sze, W.P., Yoon, W.L., Escoffier, N., & Rickard Liow, S.J. (2016). Evaluating the training effects of two swallowing rehabilitation therapies using surface electromyography: Chin Tuck Against Resistance (CTAR) exercise and the Shaker exercise. Dysphagia, 31(2), 195–205. doi:10.1007/s00455-015-9678-2
    • Yoon, W.L., Ng, W.T., & Rickard Liow, S. (2017). Swallow with Chin Tuck Against Resistance (S-CTAR): New task-specific swallowing exercise for training submental muscles. Poster, 25th Annual Meeting of the Dysphagia Research Society, Portland, USA.

    Written by Yoon Wai Lam, originator of CTAR, Director and Senior Principal Speech Therapist, B.Speech Sc. (Hons), in clinical practice since 2001. This article is for general information and does not replace an individual assessment. Contact us to arrange a swallowing assessment.

  • What Does Dysphagia from Mechanical Obstruction Sound Like?

    What Does Dysphagia from Mechanical Obstruction Sound Like?

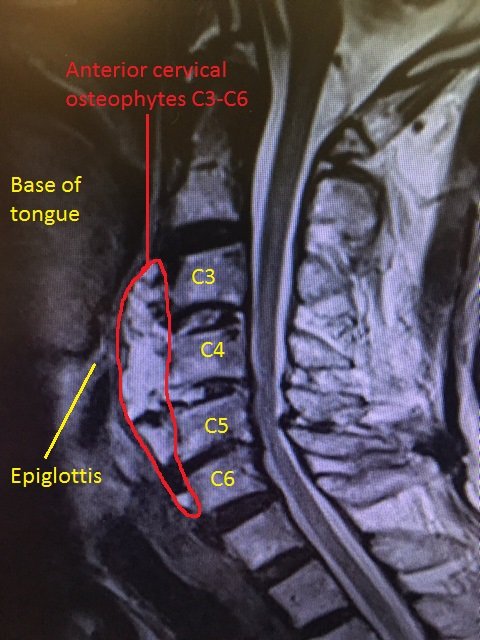
    The following patient presents with dysphagia (swallowing difficulties) secondary to the presence of prominent anterior cervical osteophytes at the level of C3-C6, most prominent at C4.

    Dysphagia symptoms include:

    • Occasional coughing noted when eating solids as well as drinking fluids.
    • Multiple swallows per bolus

    I managed to record the patient’s usual swallowing sound using my iPhone 6s. Could this be the sound of mechanical obstruction?

    osteophytes
    MRI Cervical Spine shows cervical myelopathy. Prominent anterior cervical osteophytes from C3-C6.
    osteophytes label

    The sound of patient swallowing 10ml water recorded using an iPhone 6s. Note multiple swallows & loud squish sound.

  • Worsening dysphagia. How would you manage?

    worsening of dysphagia

    A comprehensive dysphagia (swallowing disorders / difficulties) management is not only limited to diet recommendation, compensatory strategies or rehab exercises. Providing crucial feedback to the medical team is equally important.

    The following case is one case example:

    I was consulted by my speech-language pathologist / therapist colleague regarding a case of worsening dysphagia within days in a rehabilitation hospital. The patient (pt) had a stroke (left MCA infarct) diagnosed 2 weeks ago. According to the medical report from the acute hospital, the pt presents with global aphasia and dense right hemiplegia.

    Day 1:

    Initial assessment revealed mild oropharyngeal dysphagia and global aphasia. Delayed swallowing initiation was suspected. Meal supervision was performed by the ST and pt was started on soft diet and thin fluids.

    Day 2:

    Patient’s swallowing presentation appeared to have worsened. Oral control appeared poorer, and oral residues were noted post swallow. Noted reduction in hyolaryngeal elevation and double swallows per bolus. Coughed on thin fluids. Diet was downgraded to minced diet (IDDSI Level 5) and nectar-thick fluids (IDDSI Level 2) by teaspoon.

    Day 3:

    Staff nurse reported to the ST that pt is coughing on minced diet and nectar thick fluids during breakfast. On ST review, it was noted that patient presents with tongue pumping with significant amount of oral residue post swallow, delayed swallowing initiation, and multiple swallows per bolus. Wet voice was noted post swallow.

    I was asked by my colleague for a second opinion.

    **Before I move on to explain our plan for the case, allow me to list the suggestions by some of the SLPs I spoke to when I presented the case to them.


    1) Most SLPs would want to refer the patient for an objective assessment [Videofluoroscopy (VFS) or Fiberoptic Endoscopic Examination for Swallowing (FEES)].


    2) Some would want to downgrade the diet accordingly to patient’s presentation and observe as so far no other professionals have reported any significant changes. 


    3) Some would want to inform the team doctor regarding the worsening dysphagia, and to rule out the potential underlying medical complications. 

    I asked my SLP colleague the following questions:

    Question 1: What are the possible causes of worsening dysphagia? 

    Answer: Maybe stroke, and maybe other new neurological deficits. 

    Question 2: Why do you think no one else notice any other changes in status except you? 

    Answer: Not sure. That’s why I am worried that I am wrong. 

    My answer: The patient has dense hemiplegia (power = 0) and global aphasia. Unlikely for anyone else to have noticed any changes functionally as both limbs and language functions are 0. 

    Question 3: What would be your recommendation? 

    Answer: What if I am wrong? I don’t dare to ask for a CT scan or MRI as I could be wrong and patient may end up paying for unnecessary procedure and it is not cheap.

    Question 4: What if you are right?

    Answer: Then the medical team can treat the pt earlier. 

    Question 5: Now evaluate the pro and cons the decision “what if you are wrong?” vs “what if you are right?”. 

    Answer: Ok I think it would be better to discuss with team doctor and seek their opinion on this. Will suggest further assessment to rule out new events (such as stroke / neuro issues)

    After discussion with the doctor, patient was sent to the acute hospital for urgent CT scan. The new CT scan showed hemorrhagic conversion on the left MCA infarct (worsening of the stroke).

    In summary, when we encounter rapid progression of dysphagia, perhaps it would be better to speak to the team doctor to find out the cause(s). Objective swallowing assessment should be deferred until patient’s medical status is stabilized.
